

⚡ Quick Reference Summary
- Not Classic Photosensitivity: Spironolactone does not typically cause immediate, severe sunburns or rashes like other photosensitising drugs (e.g., hydrochlorothiazide or tetracyclines).
- Impaired DNA Repair: The primary concern is spironolactone's impact on the cellular repair mechanism for UV-induced DNA damage, specifically by depleting the XPB protein.
- Accelerated Ageing & Damage: This impairment means your skin is less efficient at fixing damage from sun exposure, potentially leading to accelerated photoageing and accumulated cellular damage over time.
- Label Context: Neither the US FDA label nor the current Australian CMI leaflet for Aldactone (spironolactone) mentions sun sensitivity; the scientific understanding of its DNA repair impact emerged decades after the drug's initial approval.
- Skin Cancer Risk: Large-scale studies involving millions of patients have generally not found a statistically significant increase in overall skin cancer risk directly attributable to spironolactone use.
- Highest Risk Group: Young, fair-skinned women taking spironolactone for acne, often with active outdoor lifestyles, face the highest cumulative risk due to chronic, repeated UV exposure and impaired repair.
- Protection is Key: Proactive sun protection, especially physical barriers like UPF 50+ clothing and UV-Blocker umbrellas, is crucial to minimise UV damage and support your skin's health.
Spironolactone (sold in Australia as Aldactone and Spiractin, as well as generic brands) doesn't usually cause the fast, exaggerated sunburn of classic photosensitising drugs. The concern is subtler: research suggests it depletes XPB, a protein skin cells need to repair UV-damaged DNA. In Australia, where UV levels are among the highest in the world and, as Safe Work Australia notes, can be hazardous year-round rather than only in summer, that slower repair is worth taking seriously.
In the US, spironolactone ranks as the 52nd most prescribed drug, with pharmacies dispensing 12.8 million prescriptions to 3.5 million patients annually. It is used for conditions ranging from hypertension and heart failure to hormonal acne and polycystic ovary syndrome (PCOS). In Australia, the approved uses listed for Aldactone include high blood pressure, fluid build-up (oedema) linked to heart failure and other conditions, primary hyperaldosteronism and hirsutism. With so many people taking it, questions about side effects come up often, and sun sensitivity is among the most common.
However, the information available online is often conflicting, with many resources either dismissing the concern entirely or confusing it with the classic photosensitivity caused by other medications like hydrochlorothiazide (often co-prescribed) or certain antibiotics. The brief, often superficial answers typically found online lack the crucial medical and biological context needed for patients to make informed decisions. This article aims to cut through the confusion and provide a deeper, research-backed understanding of spironolactone's interaction with sun exposure.
The truth behind spironolactone "sun sensitivity" involves a sophisticated cellular mechanism related to DNA repair impairment rather than the immediate, visible reactions of classic photosensitivity. Understanding this fundamental distinction is vital for patients and healthcare providers alike. It empowers individuals to adopt effective, targeted sun protection strategies, mitigate potential long-term risks, and continue to benefit from this important medication while protecting their skin health. As a brand founded by melanoma survivor Ron Walker, UV-Blocker is committed to providing accurate, actionable information on sun protection, and this guide also covers what spironolactone users need to know under Australian UV.
Does Spironolactone Sun Sensitivity Actually Exist?
Yes, spironolactone can indeed lead to a form of sun sensitivity, but it's critical to distinguish it from the more commonly understood phenomenon of "photosensitivity." Classic photosensitivity, often associated with drugs like tetracycline antibiotics, non-steroidal anti-inflammatory drugs (NSAIDs), or diuretics such as hydrochlorothiazide, typically manifests as a rapid, exaggerated sunburn response, severe rash, blistering, or itching upon sun exposure. These reactions usually occur quickly after being in the sun, sometimes within minutes to hours, and are often painful and visibly alarming.
Spironolactone's impact is subtler and operates at a deeper cellular level. Instead of causing an immediate, visible reaction, research indicates that spironolactone interferes with the skin's natural ability to repair DNA damage caused by ultraviolet (UV) radiation. This means that while you might not experience a faster or more severe sunburn on spironolactone, your skin cells are less equipped to correct the genetic damage that UV light inflicts. This impairment can lead to a cumulative effect, where uncorrected DNA damage can build up over time, potentially accelerating photoageing (premature wrinkles, sunspots, loss of elasticity) and increasing the long-term risk of certain skin conditions, even if the immediate burn response isn't heightened. It's less about sensitivity to light and more about a reduced capacity for cellular self-repair post-exposure, making comprehensive sun protection strategies even more essential for those taking the medication.
How Does Spironolactone Affect Your Skin's UV Damage Repair?
The scientific understanding of spironolactone's sun-related effects centres on its impact on a crucial protein involved in DNA repair: XPB (Xeroderma Pigmentosum Group B) protein. UV radiation, particularly UVB, causes specific types of damage to DNA within skin cells, primarily cyclobutane pyrimidine dimers (CPDs). To prevent these damaged DNA segments from leading to mutations or cell death, our cells have sophisticated repair mechanisms, most notably the Nucleotide Excision Repair (NER) pathway.
The XPB protein is an integral component of the NER pathway. It functions as a helicase, unwinding the DNA helix around the site of damage, which is a necessary step for the repair machinery to cut out the damaged segment and synthesise a new, healthy one. Studies have demonstrated that spironolactone can deplete levels of the XPB protein within cells. When XPB levels are reduced, the efficiency of the NER pathway significantly diminishes. This means that cells exposed to UV radiation, while still experiencing the same initial DNA damage, become less capable of effectively repairing that damage. The consequence is an accumulation of unrepaired or misrepaired DNA lesions. This cellular vulnerability, therefore, makes individuals on spironolactone more susceptible to the long-term detrimental effects of UV exposure, even if the acute sunburn response isn't visibly altered. It's a silent vulnerability that underscores the importance of robust, consistent sun protection.
Why Don't the FDA Label and Australian CMI Mention Sun Sensitivity?
The absence of explicit warnings about "sun sensitivity" or "DNA repair impairment" on the official US FDA label for Aldactone (the brand name for spironolactone) can be perplexing, especially given the emerging scientific understanding. This omission is primarily due to the regulatory process for drug approval and the timeline of scientific discovery. Spironolactone was first approved by the FDA in 1959. At that time, the primary focus of drug safety research was on acute, immediate, and easily observable adverse effects.
The intricate details of cellular DNA repair mechanisms, the specific role of proteins like XPB, and the subtle, long-term impacts of medication on these pathways were not well-understood or widely researched in the context of drug side effects during the mid-20th century. Most of the groundbreaking research detailing spironolactone's effect on XPB protein depletion and DNA repair capacity has emerged much more recently, primarily in the late 20th and early 21st centuries. The FDA's drug labels are typically based on clinical trials and post-market surveillance data available at the time of approval and significant subsequent updates. Unless new, compelling clinical evidence, particularly from large-scale human studies, demonstrates a direct and significant increase in adverse outcomes (like skin cancer) attributable to this mechanism, the label may not be updated to include such a nuanced warning. Therefore, while the scientific community has identified this mechanism, it hasn't yet translated into a prominent warning on the official drug insert, highlighting a gap between cutting-edge research and standard clinical advisories.
The same gap shows up in Australia. Here, the patient-facing document is the Consumer Medicine Information (CMI) leaflet, which healthdirect describes as covering who should take a medicine, how to take it and its known side effects. The current Aldactone CMI (prepared in June 2025) doesn't mention sun sensitivity either. It lists skin rash, itchiness, peeling skin and skin redness among the common side effects, and asks you to speak to your doctor if any of these worry you. So if nobody mentioned sun protection when you were prescribed spironolactone, that's the likely reason, not a sign that the research doesn't apply to you.
Who Needs to Be Most Careful About Spironolactone and Sun Exposure?
While all individuals taking spironolactone should be mindful of its impact on UV damage repair, certain groups face a higher cumulative risk and should exercise particular caution. Understanding these risk factors can help tailor more effective sun protection strategies.
- Young Women Prescribed for Acne or PCOS: This demographic often represents the largest group taking spironolactone. They are frequently younger, more active outdoors, and may have fair skin types (Fitzpatrick types I-III) that are inherently more susceptible to UV damage. Their active lifestyles, combined with potentially many years of medication use, mean a greater lifetime accumulation of UV exposure and consequently, more opportunities for impaired DNA repair to lead to long-term cellular damage.
- Individuals with Fair Skin (Fitzpatrick Skin Types I-III): People with lighter skin tones naturally have less melanin, which provides some inherent protection against UV radiation. They are more prone to sunburn and have a higher baseline risk for photoageing and skin cancer. The added impairment from spironolactone further elevates this risk.
- Those with Outdoor Occupations or Hobbies: Individuals who spend significant time outdoors due to work (e.g. tradies, farmers, landscapers and athletes) or leisure activities (e.g. bushwalking, gardening, surfing and beach sports) accumulate higher doses of UV radiation. Cancer Council notes that people who work outdoors receive up to 10 times more sun exposure than indoor workers. This consistent, heavy exposure, when combined with reduced DNA repair efficiency, creates a substantial risk factor for accelerated skin damage.
- Patients with a History of Skin Cancer or Precancerous Lesions: For individuals who have previously battled skin cancer (melanoma, basal cell carcinoma, squamous cell carcinoma) or have a history of numerous atypical moles or actinic keratoses, their skin cells are already more vulnerable. Adding a medication that impairs DNA repair could potentially exacerbate their existing predisposition to further UV-induced damage and recurrence.
- Long-Term Users of Spironolactone: The effects of impaired DNA repair are cumulative. Patients who take spironolactone for extended periods (several months to years) are at greater risk simply due to the prolonged duration over which their skin's repair mechanisms are compromised during repeated sun exposures.
Recognising these heightened risk factors is the first step towards implementing proactive and robust sun protection measures, which should become a non-negotiable part of their daily routine.

Does Spironolactone Increase Skin Cancer Risk?
This is arguably the most pressing question for many patients. While the cellular research indicates that spironolactone impairs DNA repair, which theoretically could increase skin cancer risk over time, large-scale epidemiological studies have largely provided reassurance. Multiple cohort studies and meta-analyses, examining millions of patient records, have investigated the association between spironolactone use and various forms of skin cancer, including melanoma, basal cell carcinoma (BCC), and squamous cell carcinoma (SCC).
For instance, a significant meta-analysis published in a dermatology journal reviewed data from several large observational studies. The overarching conclusion from such comprehensive analyses has been that there is currently no statistically significant association between long-term spironolactone use and an increased risk of melanoma or non-melanoma skin cancers (BCC and SCC). Some studies have noted a slight, non-significant trend or an association that could be confounded by other factors (e.g. concurrent use of hydrochlorothiazide, which is a known photosensitiser). However, the evidence is not strong enough to establish spironolactone as an independent risk factor for skin cancer based on current population-level data.
It's crucial to interpret this information carefully. The absence of a detected increase in population-level skin cancer risk doesn't negate the cellular mechanism of impaired DNA repair. Instead, it suggests that the human body's other protective mechanisms, or the typical duration and dosage of spironolactone, may sufficiently mitigate this theoretical risk, or that the increase is too small to be statistically significant in these large observational studies. Nonetheless, a proactive approach to sun protection remains a wise strategy, especially given the chronic nature of sun exposure and the importance of preventing photoageing and other forms of UV damage.
How Should Spironolactone Users Handle Sun Sensitivity Protection?
Given the nuanced understanding of spironolactone's effect on DNA repair, a comprehensive and proactive sun protection strategy is paramount for all users. This isn't just about preventing sunburn, but about minimising the cumulative cellular damage that your skin is less equipped to repair. Here are actionable steps:
-
Embrace Physical Sun Protection: This is the most effective defence against UV radiation, as it creates a physical barrier that blocks rays before they can reach your skin.
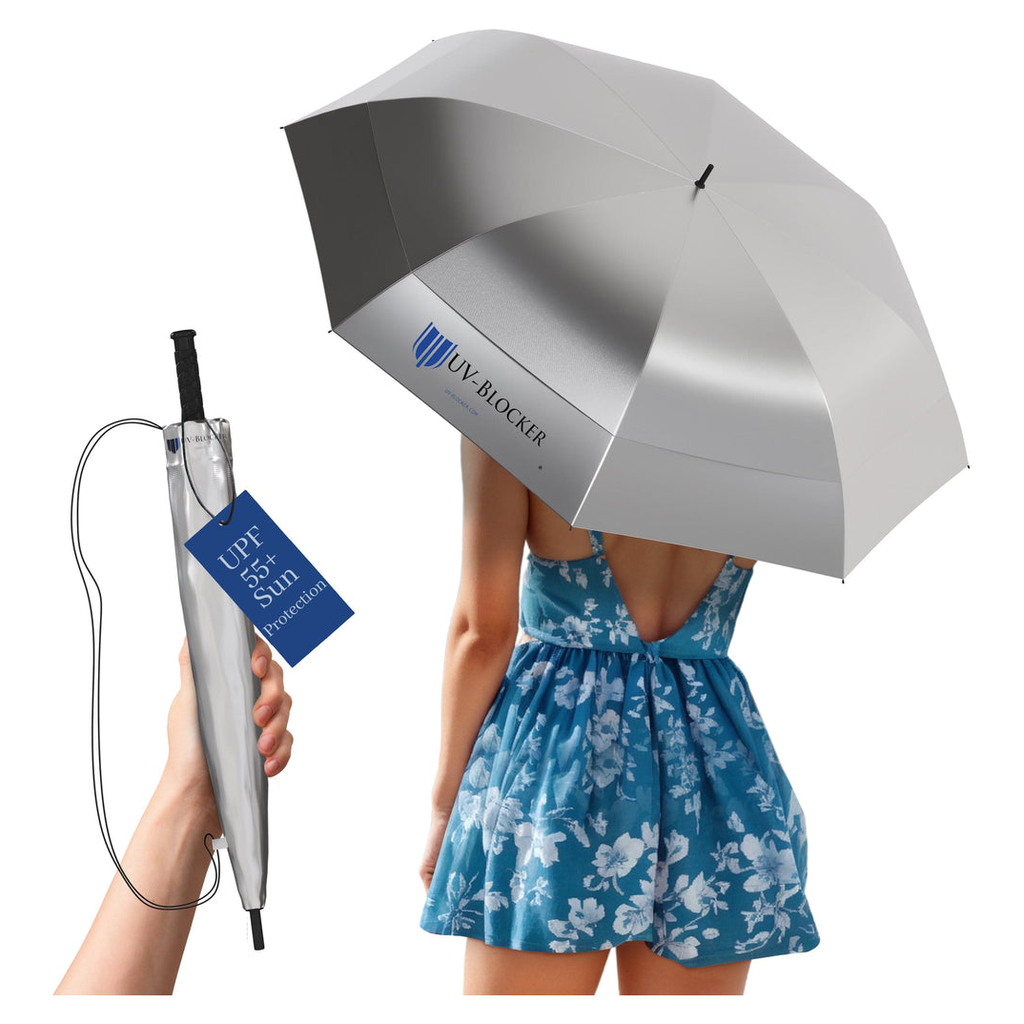
- UV-Blocking Umbrellas: A UPF 50+ umbrella from UV-Blocker, made with Solarteck® fabric, gives you shade you can carry. Unlike sunscreen, which can wear off, an umbrella provides consistent shade over the area it covers. The fabric is lab-tested (AATCC TM183-2020) to block 100% of UVB and 99.97% of UVA, and UV-Blocker umbrellas are approved by the Melanoma International Foundation, which makes them a practical choice for walks, outdoor events or simply sitting on the deck. Learn more about the benefits of physical sun protection.
- UPF 50+ Clothing: Opt for clothing with an Ultraviolet Protection Factor (UPF) of 50+. This includes long-sleeved shirts, long pants and broad-brimmed hats. These items are specifically designed to block over 98% of UV rays. In Australia, look for a UPF 50 or 50+ label tested to AS/NZS 4399, which ARPANSA rates as "Excellent protection".
- Seek Shade Strategically: Plan your outdoor activities to coincide with times when the sun's rays are less intense, typically before 10 am and after 4 pm. When outdoors, actively seek out natural or artificial shade.
- Use Broad-Spectrum Sunscreen Diligently: Cancer Council recommends an SPF50 or SPF50+, broad-spectrum, water-resistant sunscreen. Apply it liberally to all exposed skin at least 20 minutes before you go outside. Reapply every two hours, or more frequently if swimming or sweating. Mineral sunscreens containing zinc oxide and titanium dioxide are often preferred for sensitive skin.
- Wear Sunglasses: Protect your eyes and the delicate skin around them with sunglasses that block 99-100% of UVA and UVB rays and meet the Australian Standard AS/NZS 1067.
- Be Mindful of Reflection: UV rays can reflect off surfaces like water, sand, snow, and concrete, increasing your exposure even in shade.
- Regular Skin Checks: Conduct self-skin exams monthly and schedule annual professional skin checks with your GP or a dermatologist, especially if you have existing risk factors for skin cancer. Early detection is key for successful treatment.
By integrating these practices, particularly by using the consistent protection of physical barriers like UV-Blocker umbrellas and UPF 50+ clothing, individuals on spironolactone can significantly reduce their overall UV exposure and support their skin's health despite the medication's cellular effects.
Spironolactone and Sun Protection in Australia
Australia has some of the highest UV levels in the world. Cancer Council notes that UV is present every day of the year and can be high even on cool or overcast days, and that just 15 minutes of unprotected exposure when the UV Index is 3 or above can start to damage skin. For anyone whose skin may be slower to repair UV damage, that puts the focus on everyday, cumulative exposure (the school run, the walk to the bus stop, a weekend at the beach) rather than only the occasional bad burn.
Brands, your CMI and who to ask
In Australia, spironolactone is sold as Aldactone, Spiractin and generic brands. Your pharmacist can give you the CMI leaflet for your brand, and healthdirect explains how to read a CMI. If you also take hydrochlorothiazide, ask your pharmacist or GP to check your combination: hydrochlorothiazide is a known photosensitiser and can cause the classic sunburn-type reaction that spironolactone on its own usually doesn't. Never stop or change your dose without talking to your doctor first.
Practical steps under Australian UV
- Check the UV forecast every day: Sun protection is recommended whenever the UV Index is 3 or above. The free SunSmart Global UV app and the Bureau of Meteorology's UV Index forecast show the sun protection times for your location.
- Use a TGA-regulated sunscreen properly: Sunscreens sold in Australia are regulated by the TGA. Choose SPF50 or SPF50+, broad-spectrum and water-resistant, use about seven teaspoons (35 mL) for a full-body application, and reapply every two hours.
- Wear a proper hat: Cancer Council suggests a broad-brimmed, legionnaire or bucket hat that shades your face, nose, neck and ears; caps and visors don't protect enough.
- If you work outdoors: Safe Work Australia says businesses must manage the risks of working in the sun, including by providing shade and shelter, sun-protective clothing, hats, sunglasses and sunscreen. Ask what your workplace provides.
- Get to know your skin: Cancer Council recommends checking your skin regularly for new spots or changes to existing freckles or moles, and talking to your GP about your level of risk and early detection.
- Questions out of hours: The healthdirect helpline, 1800 022 222, puts you through to a registered nurse 24 hours a day.
A UPF 50+ sun umbrella, or parasol, adds shade wherever you are. UV-Blocker's Solarteck® silver fabric, with a navy blue underside, is rated UPF 50+ and lab-tested to AATCC TM183-2020 to block 100% of UVB and 99.97% of UVA. Solarteck® fabric tested by SGS to AS/NZS 4399 (UPF 50+, Excellent). It is up to 8°C cooler under the umbrella than in direct sun, and it works in the rain too. Use it alongside sunscreen, not instead of it.
Frequently Asked Questions About Spironolactone and Sun Exposure
Is spironolactone a photosensitive drug?
No, spironolactone is not typically classified as a photosensitive drug in the way that some antibiotics or diuretics are. It generally does not cause immediate, severe sunburns, rashes, or blistering upon sun exposure. Instead, research indicates its "sun sensitivity" stems from its effect on cellular DNA repair mechanisms, specifically depleting the XPB protein, which makes your skin less efficient at repairing UV-induced damage over time.
Can spironolactone cause sunburn more easily?
While spironolactone itself isn't known to directly make you sunburn more easily or severely in an acute sense, its impact on DNA repair means that the damage caused by a sunburn (or even regular sun exposure) is not corrected as efficiently by your body. This can lead to a cumulative buildup of unrepaired cellular damage, which contributes to accelerated photoageing and potentially increases long-term risks, even if the initial burn severity isn't heightened.
What are the long-term effects of sun exposure on spironolactone?
The primary long-term concern for spironolactone users is the accelerated accumulation of cellular damage from UV radiation. This impaired DNA repair can contribute to faster photoageing (e.g., premature wrinkles, sunspots, leathery skin) and potentially increase the risk of precancerous lesions and certain skin cancers over many years, although large-scale studies have not yet definitively linked spironolactone to an increased skin cancer incidence.
Should I stop taking spironolactone if I spend a lot of time in the sun?
No, you should never stop taking any prescribed medication, including spironolactone, without talking to your doctor. If you have concerns about sun exposure while on spironolactone, discuss them with your doctor. They can help you weigh the benefits of the medication against potential risks and advise on the most appropriate sun protection strategies for your lifestyle, or explore alternative treatments if necessary.
Is it safe to use topical retinoids with spironolactone and sun exposure?
Topical retinoids (like tretinoin or retinol) are known to increase skin sensitivity to the sun and make it more prone to sunburn due to increased cell turnover and thinning of the stratum corneum. Combining this with spironolactone's impact on DNA repair means that a robust and consistent sun protection regimen is absolutely critical. Many dermatologists recommend using retinoids at night and strictly adhering to daily SPF application, along with physical barriers like UPF 50+ clothing and UV-Blocker umbrellas, to mitigate combined risks.
Conclusion
The relationship between spironolactone and sun sensitivity is more complex than a simple "yes" or "no." It's not about immediate, visible photosensitivity that causes rapid sunburns, but rather a profound effect on your skin's intrinsic ability to repair the DNA damage inflicted by UV radiation. By depleting the crucial XPB protein, spironolactone can leave skin cells less equipped to correct genetic errors, leading to a cumulative burden of unrepaired damage over time.
While large-scale studies have not definitively linked spironolactone to an increased risk of skin cancer, the cellular mechanism alone provides a compelling reason for heightened vigilance. Individuals, particularly young women taking the medication for acne who often lead active outdoor lives, must adopt a rigorous and proactive approach to sun protection. This includes seeking shade, diligently applying broad-spectrum sunscreen, wearing UPF 50+ clothing, and using physical barriers like a UV-Blocker UPF 50+ umbrella with Solarteck® fabric. These tools offer consistent protection, stopping UV rays from reaching the skin in the first place and helping guard against the silent cellular damage that spironolactone users may be more susceptible to.
Understanding this distinction empowers you to make informed choices, protect your skin effectively, and continue benefiting from your medication without unnecessary fear. Always talk to your GP, pharmacist or dermatologist for advice tailored to you, and read the CMI leaflet for your brand. As a brand founded by melanoma survivor Ron Walker, UV-Blocker understands the critical importance of effective sun protection and is dedicated to equipping you with the best tools to stay sun-safe for life.
More Questions About Spironolactone and the Sun
Does spironolactone really make skin more sensitive to sunlight?
Not in the classic way. Spironolactone isn't typically classified as a photosensitising drug, and it doesn't usually cause sunburn-like or phototoxic reactions. The concern is that it may slow the repair of UV-damaged DNA, so damage can build up without an obvious burn. Read the CMI leaflet for your brand, and talk to your GP or pharmacist if you notice unusual skin reactions in sunlight.
What SPF should I use if I take this medication?
Cancer Council recommends an SPF50 or SPF50+, broad-spectrum, water-resistant sunscreen whenever the UV Index is 3 or above, reapplied every two hours. Sunscreen alone isn't sufficient for high UV exposure: combining it with physical barriers (UPF 50+ clothing, broad-brimmed hats and UV-blocking umbrellas) provides the most reliable protection. UV-Blocker's Solarteck® fabric is lab-tested (AATCC TM183-2020) to block 100% of UVB and 99.97% of UVA.
Can I still go outdoors while taking this medication?
Absolutely. Most patients can continue outdoor activities with appropriate precautions: avoid peak UV hours (usually 10 am to 4 pm), wear protective clothing, use SPF50 or SPF50+ sunscreen, and use shade whenever possible. A portable UV-blocking umbrella gives you shade wherever you go, making it a practical solution for anyone who needs consistent sun protection.
How long after stopping the medication until sun sensitivity resolves?
Classic photosensitivity from most medicines settles within days to weeks of stopping, depending on the drug's half-life and your individual metabolism. Spironolactone's effect works through DNA repair rather than a reaction to light, so ask your prescribing doctor before you scale back sun protection. In Australia, sun protection is recommended whenever the UV Index is 3 or above, whatever medicines you take.
What are the signs of a phototoxic reaction vs. a photoallergic reaction?
Phototoxic reactions look like severe, rapid sunburn — they appear within hours of UV exposure and are dose-dependent. Photoallergic reactions involve an immune response, can spread beyond sun-exposed areas, and may appear days later. Both require prompt sun avoidance. See your GP or dermatologist for diagnosis and management.
Sun Safety Essentials for Patients on Spironolactone and Other Medicines
- Check the UV Index on the SunSmart Global UV app or the Bureau of Meteorology website, and use full sun protection whenever it is 3 or above
- Wear UPF 50+ sun-protective clothing on arms and legs, not just sunscreen
- Carry a portable UV-blocking umbrella for shade on demand — especially effective during outdoor commutes, sporting events, or waiting outdoors
- Apply sunscreen to the back of hands and tops of feet — commonly missed areas that receive direct UV
- Inform your pharmacist about all medications you take so they can flag photosensitising combinations
- Ask about UV-protective window film if you drive a lot — car windows block UVB but not all UVA